
Global Pharmacy Automation System Market Report, Size, Share and Forecast 2026–2033: The Pharmacy Count Fell by Eight Thousand and Automation Grew Anyway
The global pharmacy automation system market is USD 6,180 million in 2025 and reaches USD 11,240 million by 2033 — a 7.76 per cent CAGR, USD 5,060 million of absolute growth, and a 1.82-fold expansion. Unit shipments rise from 62,400 systems to 91,500, a 4.90 per cent CAGR, so revenue per system grows from USD 99,038 to USD 122,842, or 2.73 per cent a year.
The finding. Value grows roughly half again as fast as volume, and the gap is not price inflation. It is mix and content: larger installations, more software and more service attach at fewer, bigger sites. That is what a market looks like when its buyer base is shrinking and its throughput per site is rising. The United States has almost 8,000 fewer retail pharmacies than in 2018 and lost more than 2,000 in 2025 alone — Rite Aid liquidated, Walgreens and CVS trimming — yet total US dispensing revenue hit a record USD 751 billion, up 10 per cent. Automation revenue follows scripts per surviving site and the number of central-fill nodes a system builds, not the number of stores that open.
Where the growth sits. Decentralised dispensing cabinets are the most penetrated and slowest-growing family at 6.81 per cent, because the sale has largely been made: 86.1 per cent of US hospitals use them as their primary maintenance-dose method. Central-pharmacy robotics grows at 9.54 per cent and IV and sterile compounding automation at 10.10 per cent, because those sales have not been made: only 6.5 per cent of US hospitals run a unit-dose robot, 2.0 per cent use a robot as their primary central distribution method, and 3.7 per cent use any automation for compounding sterile preparations, with 52.7 per cent reporting no IV workflow technology at all. The market's centre of gravity is moving from a sale per nursing unit to a sale per facility.
Who sells it. Three vendors disclose enough to be reconciled: Omnicell at USD 1,185 million of FY2025 revenue, up 7 per cent; BD's Medication Management Solutions at USD 835 million in the December 2025 quarter, of which a Pheonix-allocated 45 per cent is automation; and Tosho at JPY 29.5 billion. Named pools carry 46.68 per cent of the base, and 53.32 per cent sits in a private and regional residual — Capsa, ScriptPro, ARxIUM, Parata, Innovation Associates, Willach and the Japanese and Chinese specialists. The top two vendors hold 43.50 per cent between them across the whole market, and considerably more within cabinets.
What the buyer is actually paying for. Not motion — that problem was solved years ago — but proof: that the right drug went into the right package, that the dose was verified, that the controlled substance was not diverted. Barcode verification of doses sits at 73.6 per cent of US hospitals and autoverification at 73.4 per cent, while advanced analytics sits at 5.7 per cent. The 2.73-point realisation premium in this model is a bet that the analytics and platform layer gets bought over the next eight years. If it does not, the 2033 value lands near USD 10,400 million rather than USD 11,240 million, holding units constant — a USD 850 million swing from a single assumption.
The labour argument is the demand driver. With 9 per cent of hospital pharmacy technician posts and 4.3 per cent of pharmacist posts vacant in the United States, the alternative to automation is not a cheaper manual process, it is a reduced service. Ballad Health removed a picking step that consumed six to eight technician hours a day at each of twenty-one hospitals; Harris Health is building a 60,000 square foot central-fill facility to move from 5,000 to 15,000 scripts a day. The machine is being bought against a vacancy, not against a competitor.
The regional shape. North America remains largest at 38.35 per cent of 2025 value but gives up 2.9 points as its cabinet layer matures and its retail layer contracts. Asia-Pacific grows fastest at 9.62 per cent and gains 4.1 points to 31.94 per cent, driven by Japanese, Korean and Chinese hospital dispensing and packaging where unit-dose formats are standard practice. Europe holds share at 24.73 per cent, with growth from hospital centralisation and adherence packaging.
The risk that matters. Sequencing. If retail closure removes installation sites faster than central-fill construction adds throughput capacity, the bear case puts 2033 at USD 9,850 million (6.00 per cent) rather than USD 11,240 million. A one-year deferral of the cabinet refresh cycle takes about 8 per cent out of a single year and does not return the following year. Tariffs compress vendor margin on signed contracts and delay decisions by a budget cycle rather than cancelling them.
The global pharmacy automation system market is USD 6,180 million in 2025 and reaches USD 11,240 million by 2033 — a 7.76 per cent CAGR, USD 5,060 million of absolute growth, and a 1.82-fold expansion across eight years. Unit shipments move from 62,400 systems to 91,500, a 4.90 per cent CAGR. Realised revenue per system therefore rises from USD 99,038 to USD 122,842, or 2.73 per cent a year.
That decomposition is the finding, and it inverts the way this market is usually described. Volume grows at roughly two-thirds the rate of value, and the gap is not price inflation on identical hardware. It is the composition of what is being installed: more software, more service attach, more integration work, and larger configurations at fewer sites. The industry is no longer selling a dispensing machine to every pharmacy that opens. It is selling throughput infrastructure to the pharmacies that survived, to the central-fill nodes that replaced the ones that did not, and — the thinnest and fastest-growing layer — to the sterile compounding suite that four out of five hospitals still run by hand.
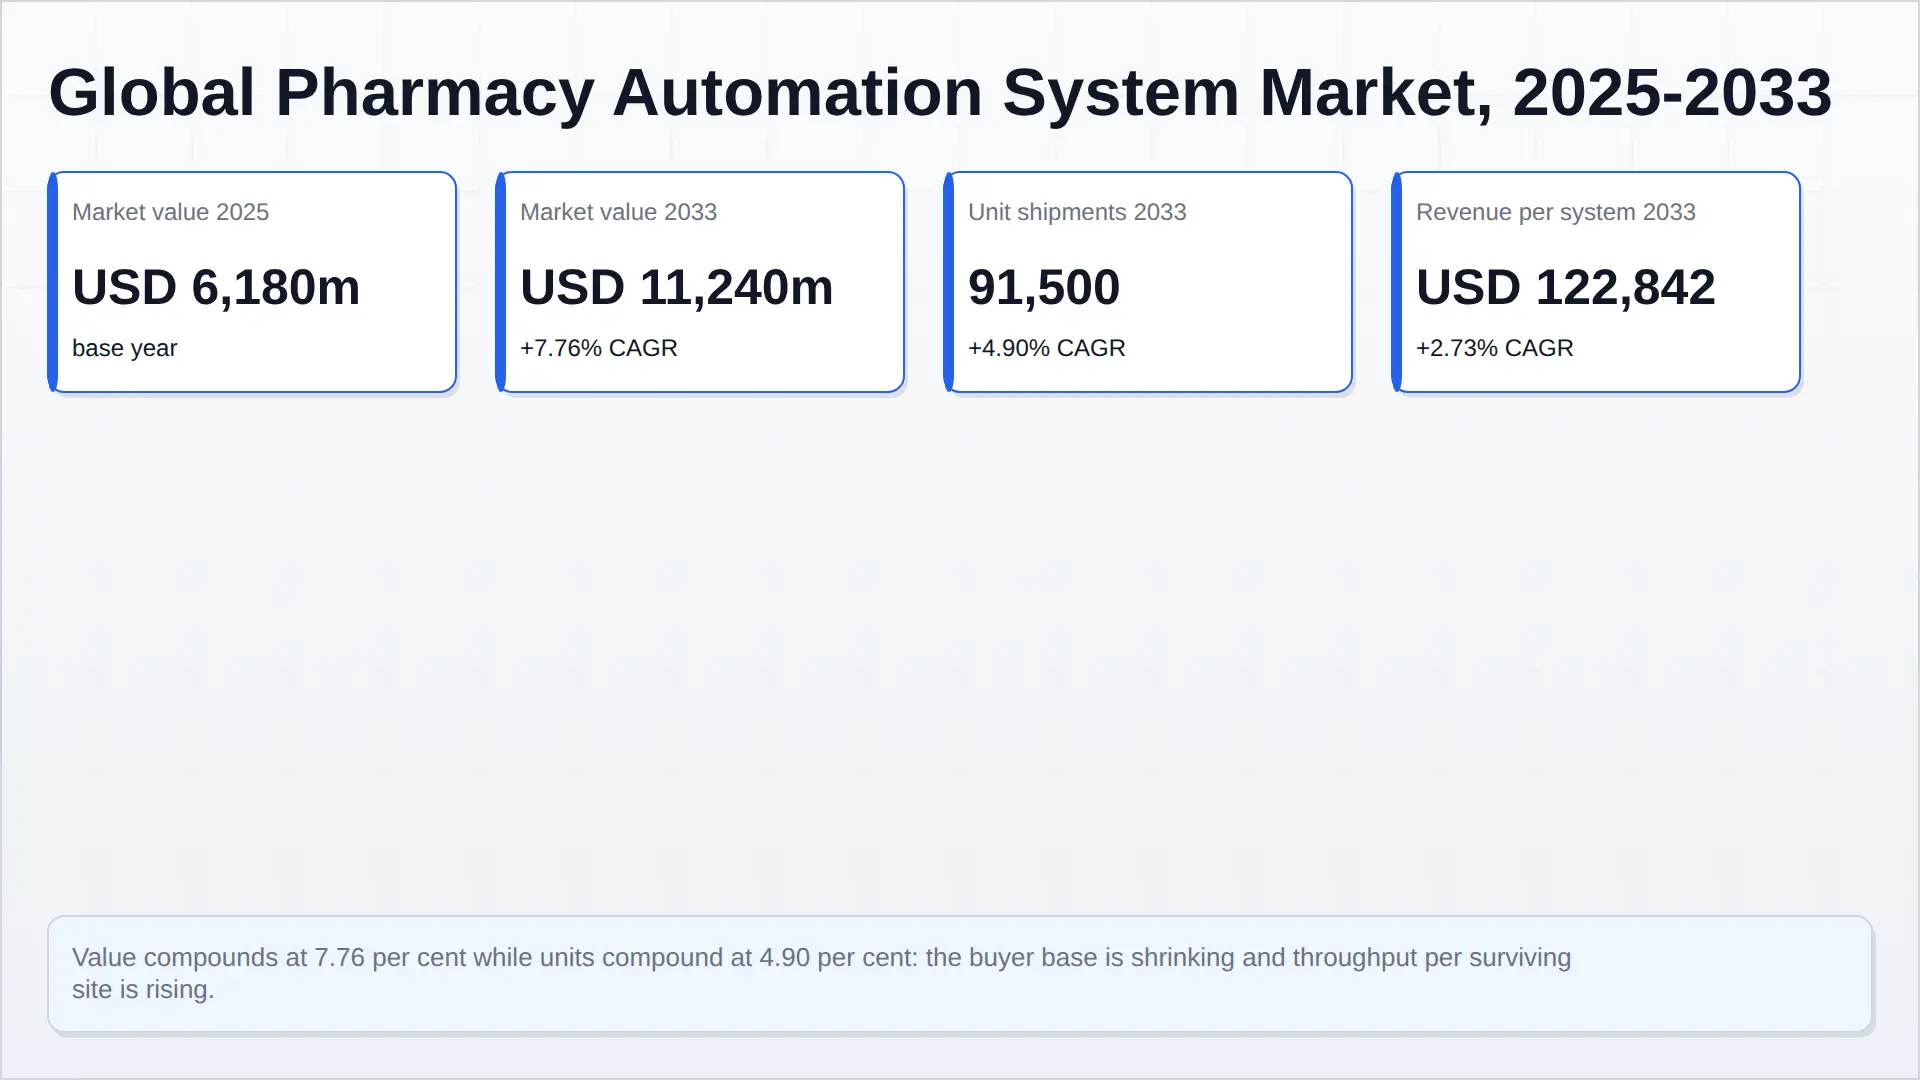
The headline model
| Metric | 2025 | 2033 | Change |
|---|---|---|---|
| Market value (USD million) | 6,180 | 11,240 | +5,060 / 7.76% CAGR |
| Unit shipments (systems) | 62,400 | 91,500 | +29,100 / 4.90% CAGR |
| Realisation per system (USD) | 99,038 | 122,842 | +23,804 / 2.73% CAGR |
| Value multiple | 1.00x | 1.82x | — |
Seven point seven six per cent is a mid-single-digit hardware cycle with a high-single-digit software and services cycle stacked on top of it. Decomposed, 4.90 points of the value CAGR come from more units and 2.73 points from more revenue per unit; the two compound to the total. Any vendor whose growth is coming only from the first number is selling into a shrinking addressable base and will not reach the second.
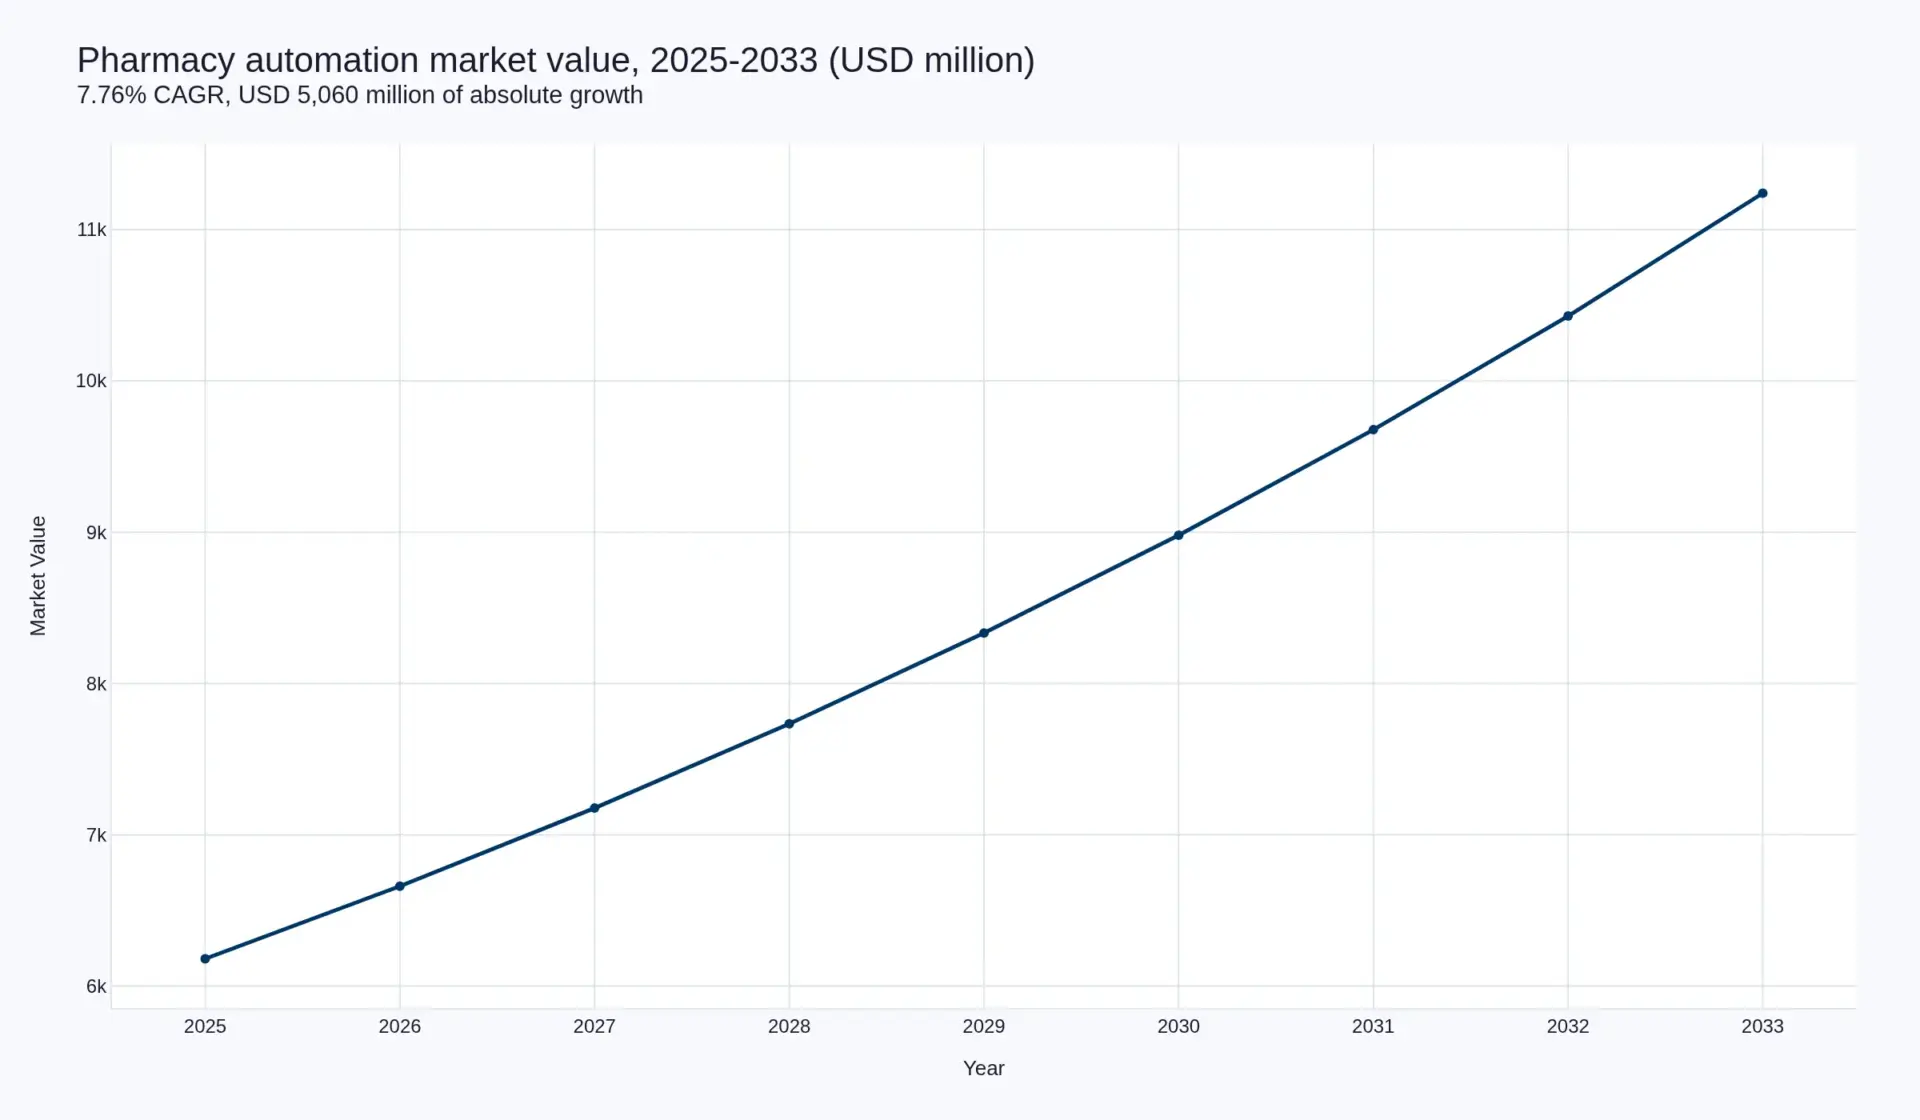
Value grows faster than units because the pharmacy count is falling
The United States has almost 8,000 fewer retail pharmacies than it did in 2018, and more than 2,000 closed in 2025 alone. Rite Aid has liquidated. Walgreens is working through a multi-year closure programme. CVS has trimmed hundreds more. Yet total US prescription dispensing revenue across all formats reached a record USD 751 billion in 2025, up 10 per cent on 2024 — record closures and record revenue in the same year.
Those two facts are not in tension once the revenue is decomposed. Growth in dispensing revenue is driven overwhelmingly by specialty drugs, and only 12 per cent of total specialty prescription revenue was dispensed through retail chains and supermarkets in 2025. Retail is where the everyday, largely generic prescription gets filled: generics are roughly 90 per cent of retail scripts, on a reimbursement that deflates. A pharmacy with thin per-script margin survives on volume, so the market consolidates toward fewer, higher-throughput sites and toward central-fill nodes that serve many sites from one robotic line.
That is precisely the shape this model describes. Automation spend is no longer a function of store openings; it is a function of scripts per surviving site, and of the number of central-fill nodes a health system or chain decides to build. A central fill replacing twenty-one entity-owned pharmacies is fewer installation sites and more automation per site — value up, units up more slowly. Harris Health's Houston central-fill build, which takes the system from 5,000 to 15,000 scripts a day in a 60,000 square foot facility, is the template. Ballad Health's consolidation of twenty-one hospital pharmacies onto a single robotic central distribution model, cutting six to eight technician hours a day per hospital out of the picking step, is the same trade seen from the labour side.
The central pharmacy is the under-automated layer
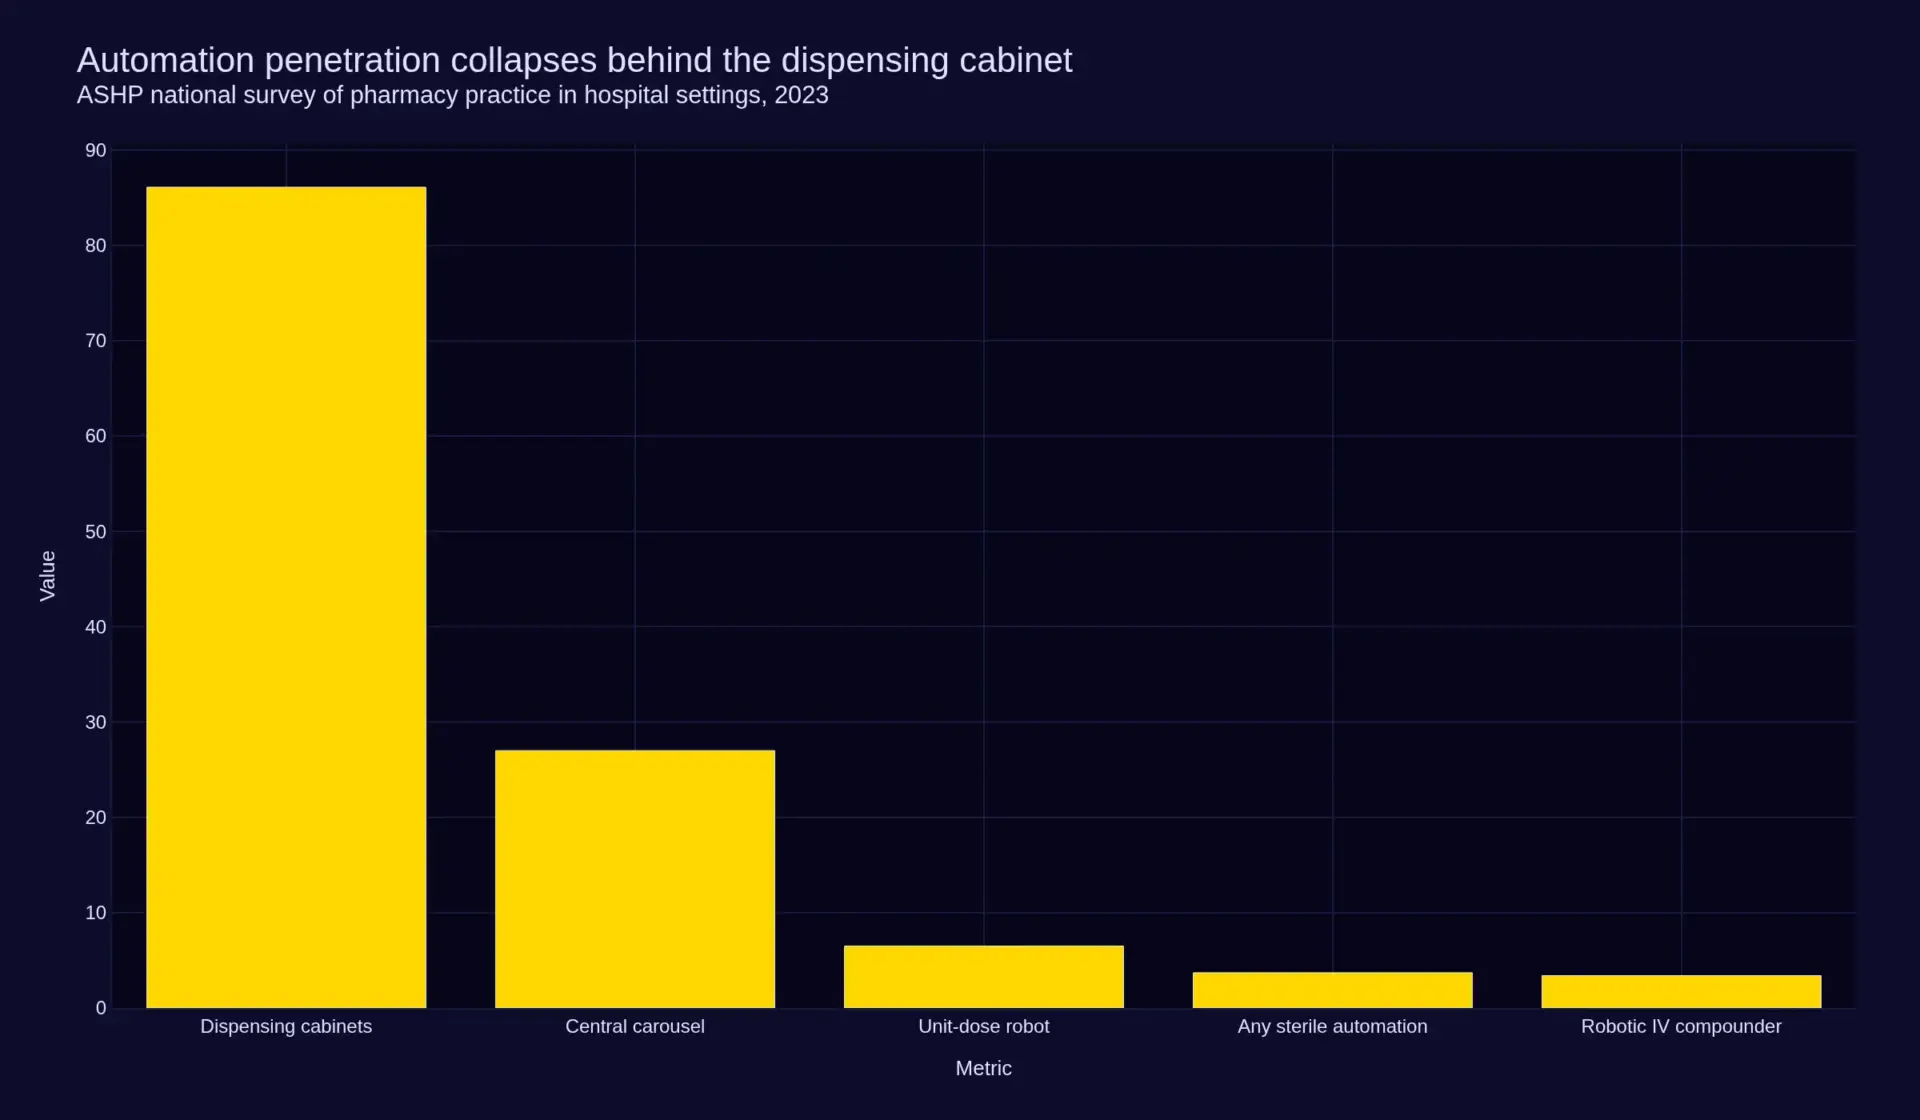
Hospital automation in the United States is deep at the point of care and shallow in the back shop. In the 2023 ASHP National Survey of Pharmacy Practice in Hospital Settings — 1,497 general and children's hospitals — 86.1 per cent used automated dispensing cabinets as the primary method of maintenance-dose distribution, and 86 per cent had adopted decentralised distribution, up from 22 per cent in 2002. Behind that front-of-house number the penetration falls away:
| Function | US hospital penetration |
|---|---|
| Automated dispensing cabinets as primary maintenance-dose method | 86.1% |
| Machine-readable coding to verify doses during dispensing | 73.6% |
| High-density carousel in the central pharmacy | 27.0% |
| Robot dispensing unit doses in the pharmacy | 6.5% |
| Automated robot as the primary central-pharmacy distribution method | 2.0% |
| Robotic IV compounding (non-hazardous) | 3.4% |
| Any automation for compounding sterile preparations | 3.7% |
The gap between 86.1 per cent at the cabinet and 2.0 per cent at the central robot is the whole commercial story of the next eight years. Cabinets are a per-nursing-unit sale that has largely been made; central pharmacy robots, carousels and IV compounders are a per-facility sale that has largely not. Set against a 9 per cent vacancy rate in hospital pharmacy technician positions and a 4.3 per cent vacancy rate in pharmacist positions, the constraint on automation is not clinical enthusiasm — it is capital, floor space and the operational disruption of rebuilding a pharmacy that cannot stop dispensing while it is rebuilt.
Regional shape
| Region | 2025 (USD m) | 2033 (USD m) | Share 2025 | Share 2033 |
|---|---|---|---|---|
| North America | 2,370 | 3,980 | 38.35% | 35.41% |
| Asia Pacific | 1,720 | 3,590 | 27.83% | 31.94% |
| Europe | 1,510 | 2,780 | 24.43% | 24.73% |
| Middle East & Africa | 300 | 430 | 4.85% | 3.83% |
| South America | 280 | 460 | 4.53% | 4.09% |
North America remains the largest region but gives up 2.9 points of share, because its cabinet layer is already built and its retail layer is contracting. Asia-Pacific gains 4.1 points and grows at 9.62 per cent, driven by hospital outpatient dispensing and inpatient unit-dose packaging in Japan, Korea and China, where strip packaging and pouch packaging are standard practice rather than an adherence add-on. Europe holds share, with growth coming from hospital centralisation in Germany, France and the Nordics and from adherence packaging in the Netherlands and the United Kingdom.
For the full regional and category build, see the Medical Devices segment hub, which carries the surrounding device reports this one is reconciled against.
Scope: what is counted, and what is excluded
This report counts revenue from five equipment families: decentralised automated dispensing cabinets; central-pharmacy robotic dispensing and automated storage and retrieval, including carousels and vertical lift modules; automated packaging and labelling, including pouch, strip and blister adherence packaging; automated table-top counting and dispensing for retail and outpatient pharmacies; and IV and sterile compounding automation, including robotic compounders and the workflow software sold with them. Hardware, embedded software, installation and the service contracts attached to the installed base are all in scope.
Three adjacent categories are deliberately excluded to prevent double counting. Consumer and home smart pill dispensers are modelled separately in the Global Smart Pill Dispenser report and never appear here. Pharmacy management and dispensing software sold standalone, without an automation device, is out of scope. Warehouse and distribution automation upstream of the pharmacy — case picking, tote handling, cold chain in the wholesaler — is out of scope, even where the same vendor sells it.
Where the automation fleet is connected and telemetered, the data layer that results sits next to the broader IoT in healthcare build, but this report counts only the device revenue and the service attached to it, not hospital networking or platform spend.
How the chapters fit together
Chapter three reconciles the model against disclosed vendor revenue: two listed vendors and one Japanese specialist carry 46.68 per cent of the base in named pools, with 53.32 per cent sitting in a private and regional residual. Chapter four walks the value chain from the linear accelerator of this market — the pharmacy floor — to the buyer, and explains why realisation per system rises while hardware bill-of-materials costs fall. Chapter five covers investment activity, including the central-fill capex wave and the portfolio separation reshaping one of the two listed vendors. Chapter six is the technology chapter, and it is where the 2.73-point realisation premium is earned or lost. Chapter seven sets out the risk cases, including the bear case in which retail closure outruns central-fill construction. Chapter eight covers device clearance, USP <797> and <800>, and the reimbursement gate that decides whether an installed machine ever gets paid for.
Articles on this market
Two companion pieces extend the analysis in this report:
- Eight Thousand Pharmacies Closed. The Machines Sold Into the Ones That Survived. — why record pharmacy closures and record dispensing revenue occurred in the same year, and why automation now follows the prescription to the survivor and to the central-fill node rather than to the store that closed.
- The Sale Has Been Made at the Cabinet and Not at the Compounding Suite — the 86.1 per cent against 3.7 per cent gap between dispensing cabinets and sterile compounding automation, and why the constraint is capital and floor space rather than clinical appetite or the rulebook.
Table of Contents
- 1. Executive summary and the headline model
- 2. Scope: what is being counted, and what is excluded
- 3. Competitive landscape: two listed vendors, one Japanese specialist, a private remainder
- 4. Value chain and cost structure: what the buyer actually pays for
- 5. Investment activity: central-fill capex and the separation trade
- 6. Technology and innovation: the machine becomes a subscription
- 7. Market risk and scenarios: closure risk, tariff risk, replacement risk
- 8. Regulatory landscape: device clearance, USP 797 and the reimbursement gate
- 9. Methodology, sources and disclosure
Competitive Landscape
Competitive landscape: two listed vendors, one Japanese specialist, a private remainder
The supplier base looks more concentrated than it is. Three vendors publish enough revenue to be reconciled against this model, and together they carry 46.68 per cent of the 2025 base in named pools. The other 53.32 per cent is private, regional or embedded inside a larger diversified manufacturer that does not break it out. That disclosure profile is the defining structural fact of the market: the buyer can price a tender precisely against three competitors and has almost no visibility into the cost base of the other twenty.
| Pool | Basis for attribution | 2025 (USD m) | Share |
|---|---|---|---|
| Omnicell | FY2025 total revenue disclosed, treated as 100 per cent in scope (pure-play medication management) | 1,185 | 19.17% |
| BD — Medication Management Solutions automation share | MMS quarterly revenue of USD 835 million annualised to about USD 3,340 million; 45 per cent allocated to dispensing and storage automation, the remainder to infusion and adjacent | 1,503 | 24.32% |
| Tosho | Net sales of JPY 29.5 billion converted at JPY 150/USD | 197 | 3.19% |
| Named pools | 2,885 | 46.68% | |
| Private and regional residual | Pheonix estimate: ScriptPro, ARxIUM, Parata, Innovation Associates, Capsa, Willach, RoboPharma, Swisslog Healthcare, Japanese and Korean specialists, Chinese domestic vendors | 3,295 | 53.32% |
Only one number in that table is hard disclosure of an in-scope pool: Omnicell’s USD 1,185 million. Tosho’s JPY 29.5 billion is hard disclosure of a near-pure-play, and the conversion is ours. BD’s line is an allocation, and the 45 per cent split is a Pheonix judgement that may be wrong by several points in either direction; it is disclosed here precisely so a reader can substitute their own. The residual is an estimate, built bottom-up from facility counts and installation rates rather than as a plug for the model, and it is the line most likely to be revised when any of the private vendors is acquired or lists.
Omnicell: the pure-play, growing at the hardware-plus-annuity rate
Omnicell reported FY2025 revenue of USD 1,185 million, up USD 73 million or 7 per cent, with product bookings and annual recurring revenue both above the mid-point of guidance. Fourth-quarter revenue was USD 314 million, up 2 per cent, carried by technical service, SaaS and expert services and consumables rather than by hardware. GAAP net income for the year was USD 2 million and non-GAAP net income USD 75 million; fourth-quarter non-GAAP EBITDA was USD 37 million against USD 46 million a year earlier.
The strategic read is in the product launch rather than the income statement. At the ASHP 2025 Midyear Clinical Meeting Omnicell launched Titan XT, its next-generation dispensing system, and framed the roadmap as a step toward “autonomous medication management” that extends beyond the pharmacy into nursing care areas. That is a direct attempt to move the sale from the central pharmacy, where penetration is low and the sales cycle is long, back into the nursing unit, where the installed base already exists and the argument is replacement rather than first purchase. Its central-fill reference, the XR2 robot at Ballad Health, is the counterweight: the same vendor selling the hub and the spoke.
BD: the diversified segment, and the portfolio separation that changes the reporting line
BD reported FY2025 revenue of USD 21.8 billion, up 8.2 per cent as reported and 2.9 per cent organic, and issued FY2026 guidance. Medication Management Solutions sits inside the Connected Care segment: MMS revenue was USD 835 million in the quarter ended 31 December 2025, of which USD 678 million was United States and USD 156 million international, against USD 801 million in the comparable prior-year quarter.
Two events matter more than the quarterly run rate. First, BD reorganised into five worldwide segments effective 1 October 2025, with Medication Management Solutions grouped under Connected Care alongside Advanced Patient Monitoring; its Biosciences and Diagnostic Solutions business was then separated and combined with Waters Corporation, completed on 9 February 2026. The remaining company is a narrower medtech business in which MMS is a more visible line, which sharpens both capital allocation and the comparability of its disclosure. Second, and more consequential for this market, BD launched the Incada Connected Care Platform — a cloud platform unifying device data — alongside the next-generation Pyxis Pro dispensing solution, and signed a first-of-its-kind US pharmacy automation partnership with Henry Ford Health to develop applications of the Rowa Vmax storage and retrieval robot.
That partnership is the clearest signal in the market this year. A health system co-developing applications on a vendor’s robot is not a capital purchase; it is a joint operating model, and it moves the competitive question from who supplies the machine to whose software defines the workflow on top of it.
Tosho: the specialist that shows what a mature automation market looks like
Tosho reported net sales of JPY 29.5 billion with 705 employees, built on dose-packaging machines and pharmacy systems since 1971, and has sold its Xana tablet packaging line into Europe since obtaining CE marking in 1997. Its scale is instructive rather than incidental: a half-century specialist with a dominant domestic position turns over a fraction of what the two US-listed vendors report, because Japanese community pharmacy automation is sold as a reimbursement-supported appliance into a market that automated early, at lower price points and higher unit volumes. The Japanese market is the closest thing to a mature end-state in this sector, and its price levels are the reason Asia-Pacific value per unit is structurally below North America’s.
The private remainder is where the competitive risk sits
Capsa Healthcare’s selection by Harris Health as design and installation partner for a central-fill build taking the system from 5,000 to 15,000 scripts a day is a reminder that the largest single installations do not always go to the largest vendors. Capsa has been in healthcare workflow for more than sixty years and is private, as are ScriptPro, ARxIUM, Parata and Innovation Associates — the vendors that dominate retail counting, outpatient pharmacy and high-volume mail and central fill respectively.
The practical implication for a buyer or an investor is that share data in this market is reconstructed, not published. Any single-vendor share figure above roughly 25 per cent should be treated with suspicion unless the definition of the market has been narrowed to one equipment family. In cabinets the top two vendors plausibly hold the majority of the US installed base. Across the whole market they hold 43.50 per cent between them, and the rest is a long tail of specialists, several of which hold a national monopoly in their home market.
How competition actually works
- Installed-base lock-in through software and consumables. A pharmacy running one vendor’s cabinets, packaging line and analytics layer faces real switching cost, and the consumables attach makes a competitor’s lower hardware price largely irrelevant over a ten-year life.
- Reference installations, not specifications. Central-fill and IV robotics tenders are decided on named references of comparable throughput. This advantages incumbents and is why a first installation at scale is worth more than a price cut.
- Group purchasing and framework contracts. In the United States the GPO contract sets the price ceiling before the clinical evaluation starts; in Europe public procurement rules set the structure of the award. In both, service response time is a scored criterion rather than a warranty term.
- Integration capability as the differentiator. The binding constraint on any installation is the interface to the electronic health record and the formulary build. Vendors that cannot staff integration lose deals they should win on hardware.
Value Chain
Value chain and cost structure: what the buyer actually pays for
The value chain in pharmacy automation is short in participants and long in consequence. Six families of equipment account for the entire market, and each has a different customer, a different floor-space requirement and a different service annuity attached to it. The mix between them, rather than the growth of any one, is what produces the 2.73-point realisation premium in the headline model.
| Equipment family | 2025 (USD m) | 2033 (USD m) | CAGR | Share 2025 → 2033 |
|---|---|---|---|---|
| Decentralised automated dispensing cabinets | 2,290 | 3,880 | 6.81% | 37.06% → 34.52% |
| Central-pharmacy robotic dispensing and automated storage and retrieval | 1,520 | 3,150 | 9.54% | 24.60% → 28.02% |
| Automated packaging and labelling | 1,180 | 2,100 | 7.47% | 19.09% → 18.68% |
| Automated table-top counting and dispensing | 690 | 1,030 | 5.14% | 11.17% → 9.16% |
| IV and sterile compounding automation | 500 | 1,080 | 10.10% | 8.09% → 9.61% |
The two fastest-growing families are the two with the lowest installed penetration, which is not a coincidence. Cabinets at 6.81 per cent and table-top counters at 5.14 per cent are mature categories growing at the rate of replacement plus densification; central robotics at 9.54 per cent and IV compounding at 10.10 per cent are growing at the rate of first installation. The market’s centre of gravity is moving from a sale that happens once per nursing unit to a sale that happens once per facility, and then again when the facility is consolidated into a hub.
What a configuration actually costs
There is no list price in this market, because no two installations are the same. The ranges below are Pheonix field estimates across North America and Europe for 2025 delivery, excluding building works and excluding the multi-year service contract:
| Item | Typical installed price band (USD) | What moves the price |
|---|---|---|
| Table-top counter / retail dispenser | 25,000 – 60,000 | Cassette count, throughput, label format |
| ADC, per cabinet | 40,000 – 90,000 | Pocket configuration, controlled-substance drawer, refrigeration |
| Carousel or vertical lift module | 150,000 – 600,000 | SKU count, height, picking automation |
| Pouch, strip or blister packaging line | 120,000 – 450,000 | Canister count, speed, multi-dose format, verification camera |
| Central-pharmacy dispensing robot | 500,000 – 2,000,000 | Throughput, drug library, redundancy, interface scope |
| Robotic IV compounder | 400,000 – 1,200,000 | Hazardous versus non-hazardous, dose range, gravimetric verification |
An enterprise cabinet deployment is not one installation; it is fifty to three hundred cabinets across a health system, phased over three to five years, each one requiring a formulary build, an interface to the electronic health record, a pocket map and a nursing workflow change. That phasing is why the installed base, not the shipment, is the right unit of analysis: the revenue per cabinet is small and the revenue per system is not.
The specification chain: who actually signs
The buyer is rarely one person. In a US health system the specification is written by a director of pharmacy or a chief pharmacy officer, priced through a group purchasing organisation contract, approved by capital finance against a payback model, and executed by supply chain. In a retail chain the decision sits with central operations and is judged on scripts per labour hour. In Japan the decision is shaped as much by the reimbursement schedule as by the vendor, because a dispensing fee attached to a machine changes the payback calculation outright.
This layered specification chain is the single most common reason a sale slips a year. It is also why service and integration capability outrank hardware specification in competitive tenders: the buyer is not buying a robot, they are buying a guarantee that the pharmacy keeps dispensing through the transition.
Where the cost sits, and where the margin migrates
Hardware bill-of-materials is a minority of the lifetime value of an installation. Motion components, sheet metal, cassettes and vision systems are procured from a small set of suppliers and have deflated in real terms as volumes rose and as Asian contract manufacturing took share. What has not deflated is the software and service layer:
- Hardware and installation. The lowest-margin layer. Competitive tenders in Europe and Japan routinely clear at low single-digit hardware margin.
- Software and integration. Formulary analytics, inventory optimisation, controlled-substance diversion detection, EHR interfaces. Sold as a licence or, increasingly, as a subscription.
- Service and uptime. A contracted annuity for the life of the machine, typically eight to twelve years. Twenty-four-hour parts availability is a condition of the sale rather than an upsell, because a central robot that stops stops the pharmacy.
- Consumables. Packaging film, canisters, labels, cassettes and printer stock. Small per unit, high attach rate, defensible against competitors who did not install the machine.
This is why the two listed vendors in this market report recurring revenue as a primary metric, and why a new entrant selling a cheaper box frequently loses on lifetime cost. The machine is the entry ticket; the annuity is the business.
The labour arithmetic that closes the sale
Payback is argued in technician hours, not in error rates, because technician hours are the line item a chief financial officer can see. The arithmetic in a consolidated health system is compelling. Ballad Health, consolidating twenty-one hospital pharmacies onto a central distribution model, removed the step in which six to eight technicians spent roughly four hours a day pulling medications from central shelves for distribution to each hospital. Harris Health’s central-fill expansion is designed to move from 5,000 to 15,000 scripts a day in a single 60,000 square foot facility. Neither project was justified on capital cost; both were justified on the labour that could not be hired.
That is the correct frame for the whole market. With 9 per cent of hospital pharmacy technician positions and 4.3 per cent of pharmacist positions vacant in the United States, the alternative to automation is not a cheaper manual process. It is a closed service. The machine wins the comparison against a vacancy, not against a competitor.
Realisation per system, decomposed
Realisation rises from USD 99,038 to USD 122,842 per system across the window. Three things drive it, in order of contribution: a shift in the mix toward central robotics and IV compounding, which carry five to twenty times the price of a counter; a higher software and service content per installation; and a modest nominal price increase on comparable hardware, largely carried by the vision, verification and analytics modules that did not exist a decade ago. Strip out the mix effect and the like-for-like price increase is low single digit — this is not a pricing-power market, it is a content-per-installation market.
Investment Activity
Investment activity: central-fill capex and the separation trade
Two different pools of capital matter in this market and they are usually discussed as one. The first is the buyer’s capital budget: a health system or a pharmacy chain deciding to rebuild a pharmacy. The second is the vendor’s capital allocation: research and development, service infrastructure, acquisitions and portfolio surgery. In 2025 and 2026 both pools moved in the same direction, which is the reason the investment trend in this market is rising rather than merely stable.
The buyer side: central fill as a capital project
Central fill is where the discretionary money is going, because it is the only configuration in which the payback is legible to a chief financial officer. Harris Health’s decision to build a 60,000 square foot automated central-fill facility designed for 15,000 scripts a day, against a legacy operation running 5,000, is a capital project with a staffing line item attached to it: the volume triples, the picking labour does not. Ballad Health’s consolidation of twenty-one entity-owned pharmacies onto a robotic central distribution model produced the same arithmetic at smaller scale — six to eight technicians spending about four hours a day on a picking step that the robot now performs.
Three characteristics of this capex are worth holding onto. It is lumpy — a single decision can be worth several million dollars of equipment and several years of service. It is infrastructure, not consumables, so it defers under financial stress before anything else does. And it is often justified on a labour market that does not exist: with 9 per cent of hospital pharmacy technician posts vacant, the alternative to the capital project is a service that cannot be staffed, which makes the investment case more defensive than it looks.
Against that, hospital capital budgets are not expanding. The projects that proceed are those where the labour saving is contractual and quantified before signature, and those where a consolidation decision — closing a hospital pharmacy and serving it from a hub — has already been taken for other reasons. Central-fill investment therefore tracks health-system merger activity more closely than it tracks device demand.
The vendor side: portfolio surgery at the largest player
BD’s fiscal 2025 closed with revenue of USD 21.8 billion and a portfolio in motion. The company reorganised into five worldwide segments effective 1 October 2025, grouping Medication Management Solutions under Connected Care with Advanced Patient Monitoring, and then separated its Biosciences and Diagnostic Solutions business into a combination with Waters Corporation, completed on 9 February 2026. For this market the consequence is not the transaction itself but the reporting line: a narrower BD makes MMS a more visible and more comparable business, and a more visible business attracts a different kind of capital-allocation scrutiny.
The same period saw BD commit capital to pharmacy automation in a form that is neither acquisition nor ordinary research spending: a co-development partnership with Henry Ford Health around the Rowa Vmax pharmacy robot, described as a first-of-its-kind collaboration in the United States. Co-development arrangements are how a vendor buys a reference installation without buying a company, and they are a leading indicator that the North American central-pharmacy segment is being contested.
At Omnicell, the capital story is one of reinvestment inside a tight margin. FY2025 non-GAAP net income was USD 75 million on revenue of USD 1,185 million, with fourth-quarter non-GAAP EBITDA of USD 37 million against USD 46 million a year earlier. That is a business funding a platform transition — Titan XT, autonomous medication management, expert services — out of a modest operating margin, which explains the emphasis on annual recurring revenue in its disclosure. A hardware-led recovery would show up as bookings; a platform transition shows up as recurring revenue, and the company is reporting the latter.
Where the acquisition money would go
The private tail of this market is the obvious consolidation pool, and the logic of any deal is the same in every case: buy the installed base, then sell the recurring layer onto it. The targets that fit that logic are the ones holding sticky positions in a single equipment family or a single geography — retail counting, outpatient pharmacy, mail and central fill, Japanese and Korean packaging, and the European carousel and storage specialists.
Two constraints keep the deal count low. First, the strategic buyers are few and are currently preoccupied with their own portfolio questions. Second, the assets that would be most valuable strategically — installed bases with a long service tail — are frequently family- or sponsor-owned businesses whose owners price them on the annuity rather than on current hardware revenue.
Capital intensity overall remains medium: assembly is not a heavy industry, and the working capital is in inventory and receivables rather than in plant. What is capital-hungry is the service network, because uptime guarantees on a machine that stops a pharmacy require parts depots and field engineers in every market a vendor sells into. That is the structural reason this market consolidates around vendors with density in a region rather than around vendors with the best machine.
Technology & Innovation
Technology and innovation: the machine becomes a subscription
Pharmacy automation is a mechanical business that has quietly become a verification business. The motion problem — pick this package and put it there — was solved at industrial quality two decades ago. What the buyer pays a premium for now is proof: that the right drug went into the right package, that the dose was checked, that the controlled substance was not diverted, and that a record exists which satisfies an inspector. Every one of the innovation fronts below is a variation on that theme, and it is the reason revenue per installed system rises 2.73 per cent a year while the bill of materials for the same motion hardware falls.
The verification stack, and how thinly it is deployed
The ASHP 2023 survey gives the clearest available picture of what hospitals have actually installed, as opposed to what vendors offer. The pattern is consistent: verification at the point of dispensing is common, verification inside the compounding suite is rare.
| Verification technology | US hospital adoption (2023) | What it changes |
|---|---|---|
| Autoverification in the electronic health record | 73.4% | Removes the pharmacist’s manual order check for routine doses |
| Machine-readable coding to verify doses during dispensing | 73.6% | The baseline proof layer for every dispensed unit |
| Barcode scanning to verify ingredients in sterile compounding | 53.6% | Prevents wrong-drug and wrong-diluent errors at preparation |
| Image or video capture of the compounding process | 38.6% | Retrospective evidence for a preparation already made |
| Compounded sterile preparation workflow software | 31.0% | Structures the record before the dose is made |
| Gravimetric verification of dose, amount and volume | 7.7% | Confirms the dose was actually drawn, not just scanned |
| Advanced analytics, including machine learning and predictive models | 5.7% | Demand forecasting, diversion detection, inventory optimisation |
| Robotic IV compounding (non-hazardous) | 3.4% | Removes the human hand from the hazardous and high-risk step |
Read down that table and the commercial logic of the next eight years appears. The technologies that sit on the dispensing path are broadly installed; the technologies that sit on the preparation path are not. With 52.7 per cent of hospitals reporting no IV workflow technology at all for sterile preparation, the compounding suite is where the installed base has to be built from almost nothing — which is why IV and sterile compounding automation grows at 10.10 per cent against 6.81 per cent for cabinets.
The 2025–2026 product cycle: platform, not machine
Both listed vendors launched into the same thesis within a quarter of each other. BD released the Incada Connected Care Platform, a cloud platform that unifies device data into a single environment, and paired it with the next-generation Pyxis Pro dispensing solution to create enterprise-wide visibility across cabinets, infusion devices and the pharmacy. Omnicell launched Titan XT at the ASHP 2025 Midyear Clinical Meeting, describing it as a step toward “autonomous medication management” that combines automation with intelligence and extends beyond the pharmacy into nursing care areas.
Neither launch is primarily a hardware event. Both vendors are trying to change the unit of sale from a device to a data layer that controls a fleet of devices across an enterprise. Three consequences follow. Software revenue becomes recurring rather than a one-off licence. The competitive comparison shifts from throughput and footprint to interoperability and analytics. And the vendor that owns the data layer can price hardware aggressively, because the annuity is no longer attached to the machine.
The Henry Ford Health partnership is the same logic expressed as a contract. A health system co-developing applications on BD’s Rowa Vmax storage and retrieval robot is buying into a shared roadmap rather than a capital asset, and it gives the vendor a North American reference for a robot that has been strongest in European and Japanese central pharmacy installations.
Central fill: the architecture that decides the unit economics
Central fill is the most consequential architectural choice in this market, because it determines how many machines a given volume of prescriptions requires. The model is hub-and-spoke: one robotic dispensing and storage line prepares and labels doses for many sites, and automated dispensing cabinets at the spoke sites hold the last mile of inventory. Harris Health’s build takes a legacy operation with rising prescription volumes, outdated picking robotics and an overcrowded facility, and replaces it with a 60,000 square foot central-fill operation designed for 15,000 scripts a day against a current 5,000. Ballad Health’s version runs the same architecture across twenty-one hospitals and removed a picking step that had consumed six to eight technician hours a day at each site.
The technology constraint in central fill is not the robot’s speed; it is the interface between the hub’s pharmacy information system and the spoke’s cabinet inventory. Every additional site in the network adds an integration and a replenishment rule, and the operating cost of the network scales with sites rather than with scripts. This is why the leading vendors sell the hub and the spoke together, and why a health system that buys a hub from one vendor and cabinets from another pays for it twice.
Where the automation is still genuinely hard
- Hazardous sterile compounding. USP <800> containment, dose accuracy and operator safety combine into a specification that few machines clear. The result is a 3.4 per cent robotic penetration rate despite fifteen years of commercially available devices.
- Unit-dose robotics for oral solids. Packaging a variable drug library into unit doses at pharmacy-level accuracy remains mechanically harder than picking a pre-packaged item, which is why only 6.5 per cent of hospitals run a unit-dose robot and 2.0 per cent use one as their primary distribution method.
- Interoperability. Device data standards in pharmacy remain proprietary in practice. A health system running three vendors’ equipment needs three integrations, and the analytics that would justify the platform sale cannot be assembled without them. That is the structural reason advanced analytics adoption sits at 5.7 per cent while barcode verification sits at 73.6 per cent.
- Diversion detection. Fifty-eight per cent of US hospitals now use diversion detection software to monitor controlled substances, which has pulled analytics into the pharmacy through the compliance door rather than the efficiency door.
The innovation conclusion
Innovation intensity in this market is high and patent activity is moderate — the intellectual property sits disproportionately in software, verification algorithms and workflow design rather than in novel mechanisms. That has two implications for the forecast. First, hardware deflation continues, so unit growth does not translate one-for-one into value growth. Second, the 2.73-point realisation premium depends on vendors succeeding at the platform sale; if buyers resist paying for software they cannot yet integrate, that premium compresses toward one point and the 2033 value lands closer to USD 10,400 million than USD 11,240 million. The base case assumes the platform sale is made, gradually, and is tested explicitly in the risk chapter.
Market Risk
Market risk and scenarios: closure risk, tariff risk, replacement risk
Three risks can move the 2033 number by more than a billion dollars and each of them is observable before it arrives. The scenario frame below holds the volume path constant in the bear case and constant in the bull case, because unit demand is the least volatile part of the model; what moves is the realisation premium and the pace of central-fill construction.
| Scenario | 2033 value (USD m) | CAGR 2025–2033 | What has to be true |
|---|---|---|---|
| Base | 11,240 | 7.76% | Volume grows 4.90%, realisation 2.73%; central fill built at the observed pace; platform sale is made gradually |
| Bull | 12,600 | 9.31% | IV compounding crosses 10% hospital penetration by 2030; software attach accelerates; central fill construction pulls forward |
| Bear | 9,850 | 6.00% | Retail closure outruns central-fill construction; hospital capex defers one full refresh cycle; realisation premium falls to about 1.7% |
Risk one: the closure shock outruns the central-fill build
The bear case is not a technology failure; it is a sequencing failure. Retail closures remove installation sites faster than central-fill construction adds throughput capacity, and the two are not one-for-one substitutable. The United States lost almost 8,000 retail pharmacies between 2018 and 2025, more than 2,000 of them in 2025 alone. Every one of those is a table-top counter and a small packaging line that will never be replaced. The replacement revenue requires that the prescriptions land somewhere that then automates — a surviving chain store, an independent with capital, or a central-fill node. Where the prescriptions land in a low-capital independent, the automation never happens.
This is why table-top counting and dispensing is the slowest-growing family in the model at 5.14 per cent, and why its share falls from 11.17 to 9.16 per cent. If closures accelerate beyond the 2025 rate, that family goes flat rather than growing, and the bear case loses a further USD 200–300 million of 2033 value from that line alone.
Risk two: the replacement cycle is deferrable
An installed cabinet or robot has an economic life of eight to twelve years, and a health system under financial pressure can run it to fourteen. Roughly two-thirds of the cabinet base in North America was installed before 2019, which means the current refresh wave is real but not compulsory in any given year. A one-year deferral across the installed base takes approximately 8 per cent out of a single year’s value and does not return in the following year, because the replacement schedule shifts rather than bunches.
The mitigating factor is that deferral is getting harder operationally. A cabinet that has run twelve years is out of parts support, its software is out of security patching, and its interface to a current electronic health record is brittle. The refresh decision is increasingly made by IT security rather than by pharmacy operations, which pulls it forward rather than pushes it back.
Risk three: the realisation premium does not get paid
The single most fragile number in this forecast is the 2.73 per cent realisation growth. If buyers accept the platform story, it holds. If they resist paying a subscription for analytics they cannot integrate across three vendors’ equipment, hardware deflation wins and realisation grows at roughly 1.73 per cent instead. Holding the 2033 unit count constant at 91,500 systems, that single point of difference lands 2033 value at about USD 10,400 million rather than USD 11,240 million — a USD 850 million swing from one assumption.
There is direct evidence for the risk in the adoption data. Barcode verification of doses sits at 73.6 per cent of US hospitals and autoverification at 73.4 per cent, but advanced analytics, including machine learning and predictive models, sits at 5.7 per cent. The analytics layer that justifies the subscription is, today, almost absent from the installed base. The base case assumes it is bought over eight years; the bear case assumes it is bought only where it arrives bundled with a device refresh.
Risk four: tariffs and geopolitical exposure
Geopolitical exposure in this market is high and it is not primarily about end demand. Pharmacy automation hardware is assembled from motion components, electronics, sheet metal and vision systems sourced across borders, and the finished machines cross borders again to reach the buyer. A tariff regime that raises the landed cost of imported equipment does two things simultaneously: it compresses vendor margin on contracts already signed at fixed prices, and it delays buyer decisions while procurement re-tenders. Both effects are visible in the installed bases of Japanese and European vendors selling into the United States, and in US vendors selling into Asia-Pacific and Europe.
The offset is price. The buyer’s payback argument is built on labour, not on the equipment price, so a 10 per cent landed-cost increase typically delays a decision by one budget cycle rather than cancelling it. That is why this risk is scored high on exposure and moderate on the overall market, rather than high on both.
Risk five: substitution, in three directions
- Central fill substitutes cabinet density. A hub serving twenty-one hospitals needs fewer cabinets per site, not more. Every consolidation decision is good for central robotics and mildly negative for the cabinet line.
- Software substitutes hardware. Demand forecasting and inventory optimisation can reduce the number of storage units a pharmacy needs. The same subscription that lifts realisation can, at the margin, reduce the unit count.
- Home dispensing substitutes retail automation. Consumer smart pill dispensers address adherence outside the pharmacy. They are modelled separately and excluded from this report, but a structural shift of adherence management into the home would remove a reason for a retail pharmacy to invest in adherence packaging.
Risk six: reimbursement deflation and the retail margin squeeze
Generic prescriptions are roughly 90 per cent of retail script volume on a reimbursement that continues to deflate, and specialty revenue — the source of the 10 per cent growth in total dispensing revenue — is largely dispensed outside retail chains and supermarkets, with only 12 per cent of specialty prescription revenue flowing through them in 2025. A retail pharmacy whose margin per script is compressing cannot fund a counter replacement out of operating cash flow. The capital has to come from a chain’s central budget, which means the decision is made on portfolio return rather than on store-level need, and portfolio return currently favours closing the store.
What would change the call
Four observable indicators would move this forecast before the annual data does: a fall in the annual US net pharmacy closure count below 1,000; sterile compounding automation crossing 8 per cent of hospitals; a disclosed recurring-revenue share above half of revenue at a major vendor; and a central-fill order announced above 20,000 scripts a day. Any three of those together would justify the bull case. A rise in the closure count above 3,000 in a single year, with no corresponding central-fill announcements, would justify the bear case.
Regulatory Landscape
Regulatory landscape: device clearance, USP 797 and the reimbursement gate
Nothing in this market is sold without clearing three separate gates, and a vendor’s addressable market is the intersection of them. The first is device regulation: the machine itself must be cleared to be sold. The second is compounding and safety standards, which decide whether a machine is allowed to make a dose at all. The third is reimbursement and professional regulation, which decide whether the buyer is paid for the work the machine does. A vendor can clear the first two and still fail the third, which is why this chapter sits between the technology and the forecast rather than at the end of the report.
Gate one: device clearance and cybersecurity
Automated dispensing cabinets, central-pharmacy robots, packaging lines and IV compounders are regulated as medical devices in the United States and as medical devices under the EU Medical Device Regulation in Europe, with the UK on its own conformity route. In the United States most of this equipment sits in Class II and reaches market through the 510(k) pathway against a predicate device, which sets two commercial consequences: a new entrant can be blocked by the absence of a suitable predicate, and a material change to an already-cleared device triggers a new submission and a launch delay.
Since the premarket cybersecurity requirements took effect in 2023, a submission must also demonstrate that the device is designed to be cybersecure, that it has a software bill of materials, and that vulnerabilities will be monitored and patched for the supported life of the device. That requirement quietly favours vendors with long service organisations, because a patching commitment is a service obligation before it is an engineering one, and it makes the twelve-year installed life an explicit regulatory commitment rather than a commercial aspiration. It also explains why hospitals are increasingly replacing cabinets for security reasons rather than throughput reasons.
In Europe, MDR tightened clinical evidence requirements and constrained notified-body capacity. For a mature hardware category with a long installed base, the practical effect is consolidation of the certification portfolio: fewer, larger submissions covering device families, and a reluctance to keep marginal products certified. For buyers, it means the number of vendors able to supply a certified product in a given European market has narrowed.
Gate two: USP <797> and <800> — the compliance engine behind IV automation
Sterile compounding is the most tightly regulated activity in the pharmacy, and it is the reason the IV automation category exists at all. United States Pharmacopeia Chapter <797> governs sterile compounding conditions, facilities, environmental monitoring and the assignment of beyond-use dates; Chapter <800> governs hazardous drug handling and requires containment and exposure control. Compliance is enforced by state boards of pharmacy and by accreditation surveyors, and non-compliance is not a commercial inconvenience — it is a licence risk and a patient safety event.
The commercial consequence is asymmetric. Barcode ingredient verification is used by 53.6 per cent of US hospitals and workflow software by 31 per cent, but only 3.7 per cent use any automation for compounding sterile preparations and 3.4 per cent use a robotic compounder. The regulatory standard is therefore not the binding constraint on adoption — cost, floor space, dose-range flexibility and the difficulty of validating a robotic process against a manual one are. That distinction matters for the forecast: a tightening of <797> or <800> would raise adoption, but the current low penetration is a commercial and operational gap, not a compliance gap, so a regulatory change is an upside risk rather than the base case.
Gate three: reimbursement and professional regulation
The buyer’s ability to pay for a machine depends on a fee schedule that was designed before the machine existed. In Japan, community pharmacy automation spread early because dispensing and technical fees supported the investment, which is why a half-century specialist such as Tosho operates at JPY 29.5 billion of revenue in a market that automated two decades before the United States did. Where the fee is attached to a professional act rather than to a device, automation improves the margin on that act; where the fee is a flat dispensing payment under deflationary pressure — the US retail generic model — automation is a defensive necessity rather than a profit lever.
Professional regulation completes the gate. Technician-to-pharmacist ratios, technician scope-of-practice rules and the conditions under which a pharmacist may verify remotely determine how much of the workflow can be delegated to a machine and a technician rather than retained by a pharmacist. Several US states have expanded technician roles and recognised technology-assisted verification; the direction of travel is toward more delegation, which supports automation, but the pace is set state by state and is not uniform enough to model as a single variable.
Two further regimes bear on the installed base without changing its size. Serialisation and interoperable traceability requirements under the US drug supply chain security law determine what data the machine must capture and retain, and their enforcement timeline has been extended more than once. Controlled-substance regulation, including diversion-detection obligations, is now the single most effective route by which analytics gets into a pharmacy: 58 per cent of US hospitals run diversion detection software, a far higher penetration than any efficiency-driven analytics product has achieved.
What the regulatory profile means for the forecast
Regulatory complexity in this market is high, the approval pathway is multi-jurisdictional, and the compliance burden is a moat rather than a barrier to growth. It raises the fixed cost of being a vendor, which supports the observed concentration; it lengthens the installed life through patching obligations, which protects the service annuity; and it creates step-changes in demand whenever a compounding or traceability standard is revised. None of those dynamics is currently strong enough to move the base case away from the modelled 7.76 per cent, but each of them widens the tail of outcomes in the bull direction rather than the bear.